



Over the past decades, the development of ventilator-integrated software and its coupling with physiological monitoring have considerably expanded the amount of data available for the management of patients receiving long-term home non-invasive ventilation (NIV) [1]. As the number of patients treated with home NIV continues to rise [2] specialized centers face increasing challenges in performing regular in-hospital assessments, leading to an increase in use of built-in ventilator software (BVS) for patient follow-up. BVS monitoring systems now provide information on adherence, leaks, respiratory events, and ventilation parameters [3], while recent advances in telemonitoring even allow remote adjustment of ventilator settings. The reliance on BVS and telemonitoring expanded rapidly in the pandemic due to further challenges with face-to-face clinical reviews. Although these technologies offer promising opportunities to optimize patient care and healthcare organization, important questions remain regarding the reliability, interpretation, and clinical relevance of the collected data [1]. These limitations, together with the time-consuming nature of data interpretation for clinicians, probably explain the substantial heterogeneity in current NIV follow-up practices across experts and countries [4].
PRO: “don’t miss the first step”: NIV built in software to guide longitudinal NIV follow-upThe concept of effective and appropriate ventilation is inherently multidimensional, encompassing not only physiological parameters or residual respiratory events, but also, treatment adherence, leak control, upper airway patency, patient–ventilator synchrony, and the patient's subjective experience (side effects, sleep quality, health-related quality of life) [5,6]. Yet, optimal modalities for monitoring of long-term ventilated patients, especially the use of BVS data, remain a matter of debate.
In a recent international web survey of 114 clinicians, 98% of the responder's stated that they reviewed the BVS data during NIV follow-up, with 78% of the respondents reporting that this is performed in all patients, while 22% apply this only to selected patients [4]. In this survey, adherence, leaks and the apnea-hypopnea index were the three highest rated assessment and monitoring tools. BVS data can be used at different levels of precision, requiring increasing levels of expertise and time as the complexity of the analyzed data increases. Analysis of average data provides information on overall device use, leaks, and the presence of residual obstructive events, whereas longitudinal analysis allows the identification of usage patterns and temporal variations in ventilatory parameters that are often clinically informative. At the highest level of precision, analysis of flow and pressure waveforms allows the identification of, and generation of hypotheses regarding, the mechanisms underlying upper airway obstruction and patient ventilator asynchrony (PVA), thereby helping to identify the main problems encountered during NIV [3].
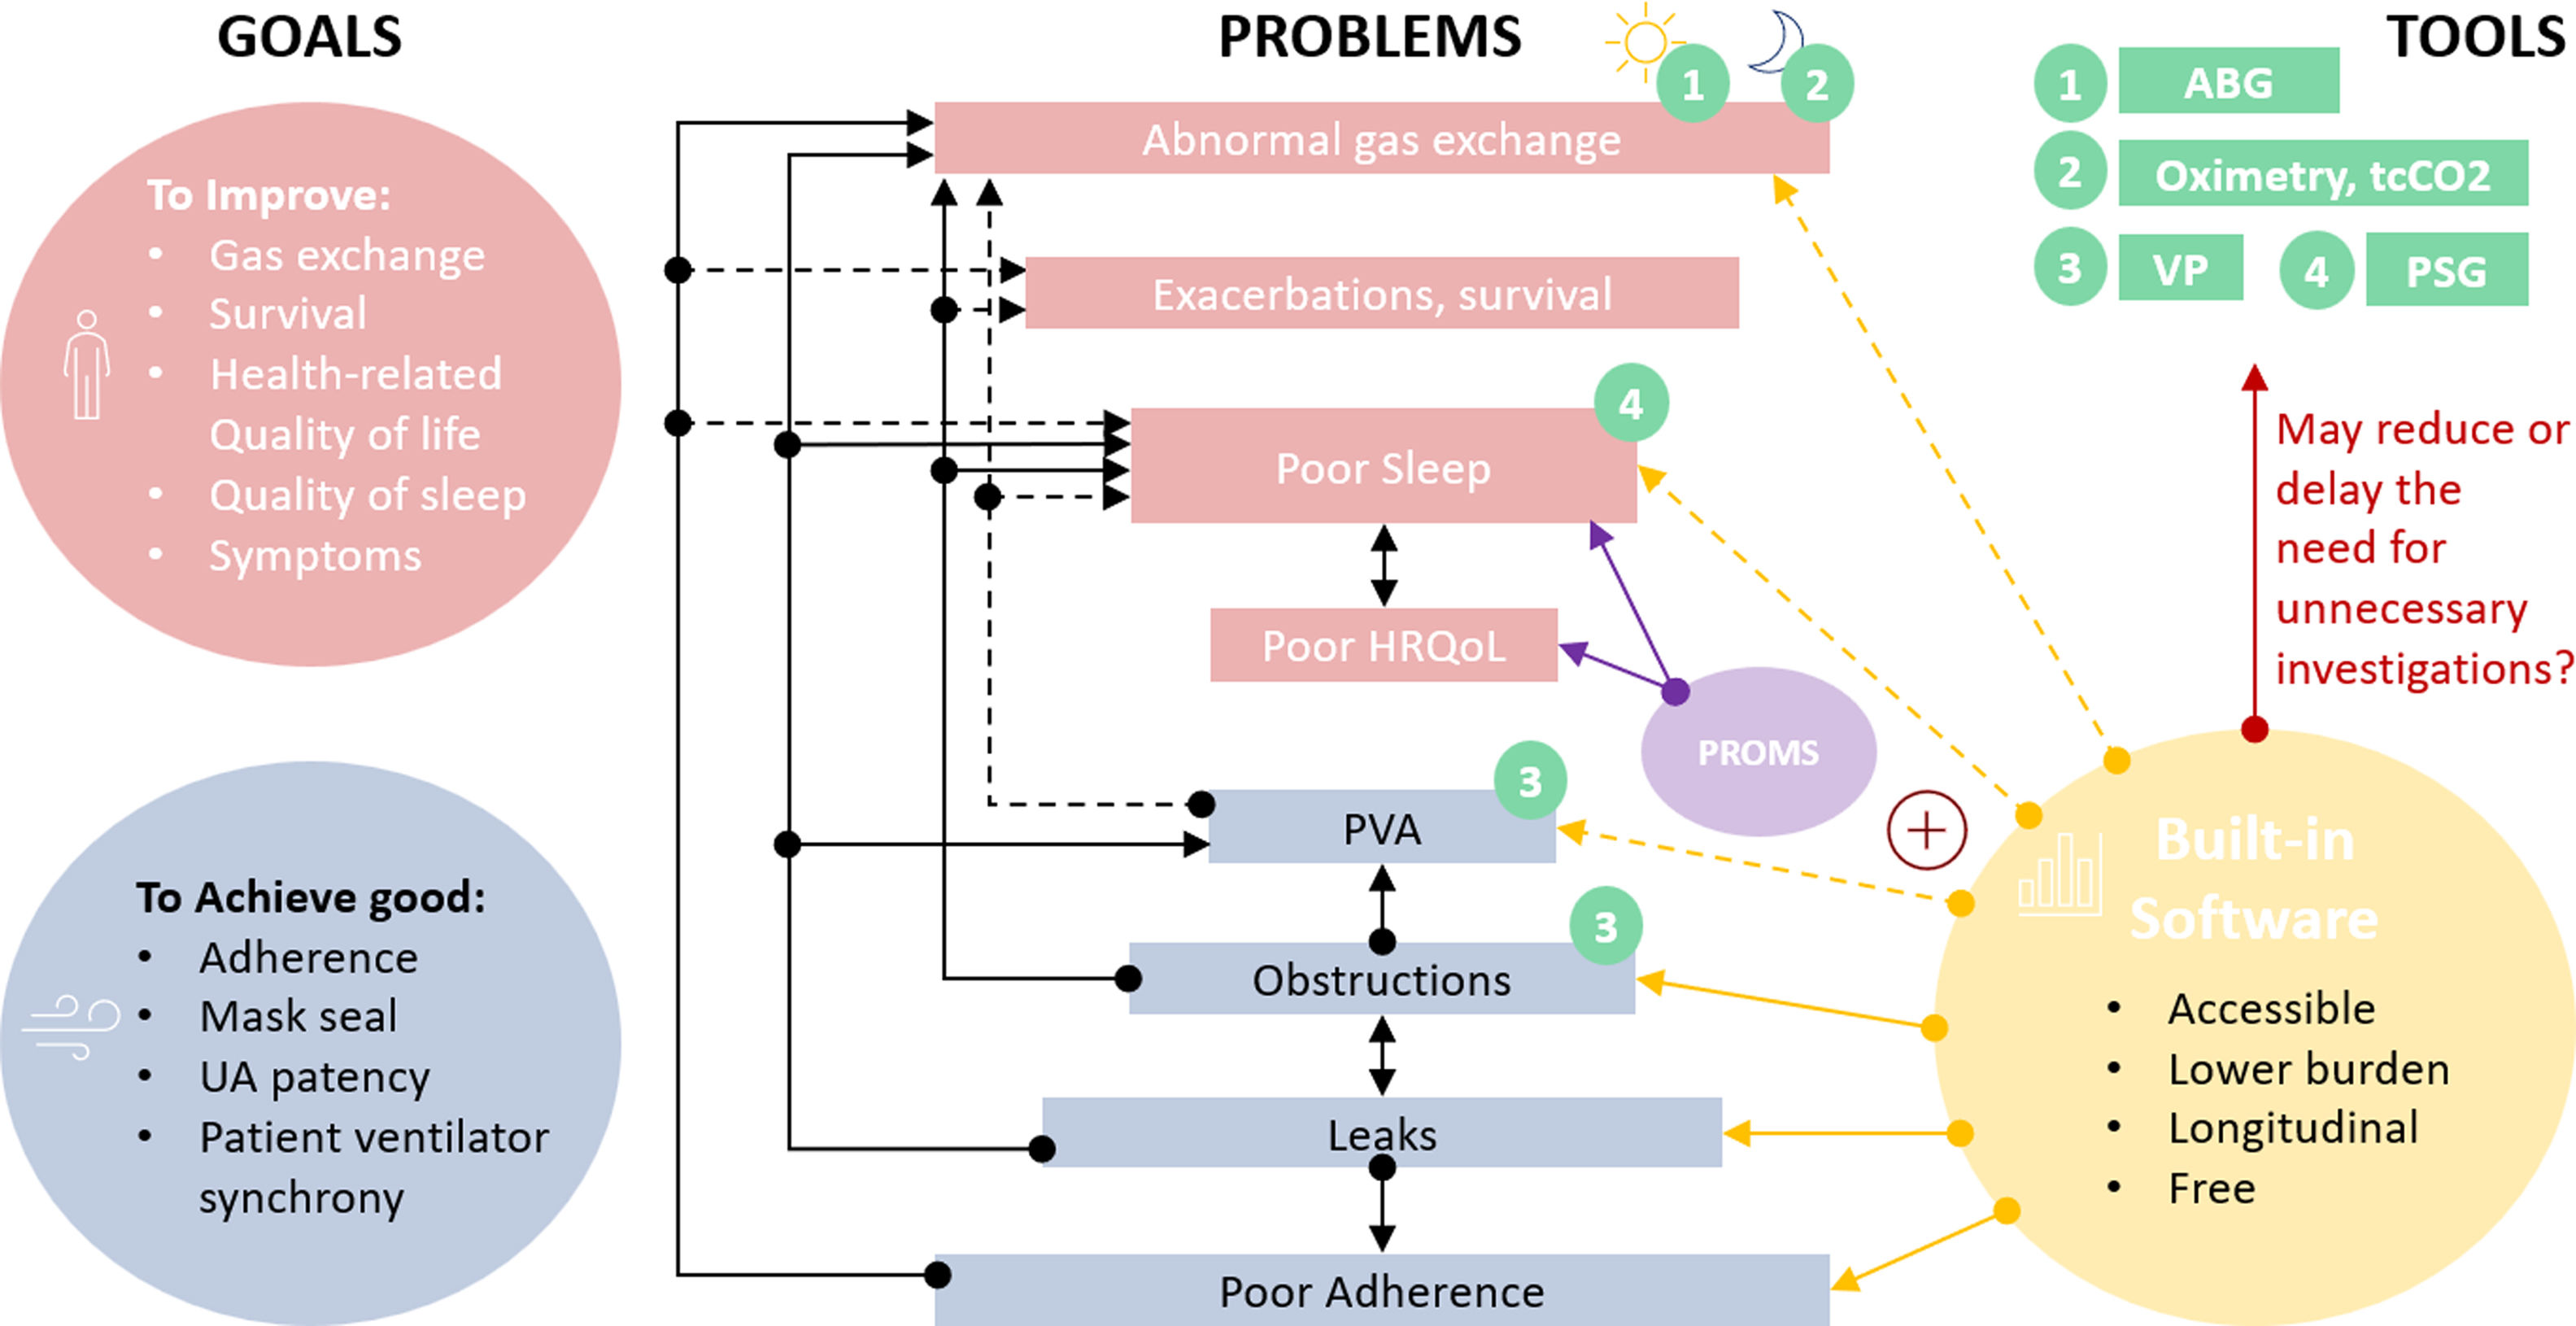
However, the current reference strategy for monitoring home NIV still primarily relies on arterial blood gas analysis and nocturnal oximetry, despite several important limitations associated with this approach [4,7]. First, these monitoring tools fail to adequately capture nocturnal respiratory disturbances with respectively 33% and 27% of examinations remaining normal despite the presence of nocturnal alveolar hypoventilation [8]. In addition, variations in SpO2 under NIV lack specificity and can reflect a wide variety of respiratory events. They may also be influenced by parameters readily available through NIV BVS, particularly treatment adherence [9] and unintentional leaks [10] (Fig. 1). Moreover, these tools fail to capture day-to-day variability or changes occurring under different conditions or device used [11,12]. Ultimately, “we only find what we actively look for”, and combined approaches incorporating BVS monitoring appear more effective than arterial blood gases and nocturnal oximetry alone in identifying ineffective home NIV [7]. Taken together, these limitations suggest that arterial blood gas analysis and nocturnal oximetry should be interpreted cautiously and, when appropriate, deferred if significant abnormalities are identified through BVS review. Moreover, they only provide a one-time, cross-sectional assessment, unlike BVS data, which enables a more comprehensive longitudinal evaluation.

Conceptual framework for the clinical use of built-in ventilator software in home NIV. Solid black arrows indicate relationships supported by published evidence, whereas dashed black arrows indicate plausible but not yet firmly established relationships. Solid yellow arrows indicate problems that can be reliably assessed using built-in ventilator software data, whereas dashed yellow arrows indicate problems that can only be assessed indirectly or with lower reliability. ABG, arterial blood gas; HRQoL, health-related quality of life; PSG, polysomnography; PROMs, patient-reported outcome measures; PVA, patient–ventilator asynchrony; tcCO2, transcutaneous carbon dioxide monitoring; UA, upper airway; VP, ventilatory polygraphy.
BVS data enables the detection of the main events responsible for nearly 80% of NIV failures and can also provide valuable insights into certain PVA, thereby supporting their integration into structured management algorithms such as those proposed by the SomnoNIV Group [3,5,7]. Early remote assessment of ventilator data downloads can help optimize patient ventilation by identifying modifiable factors, particularly interface leaks and inappropriate ventilator settings [13,14]. Indirect markers of insufficient ventilation derived from BVS monitoring (such as intracycle respiratory efforts, measured respiratory rate exceeding backup respiratory rate, tidal volume, and residual AHI) may also provide useful information for optimizing ventilator settings [15]. Future studies may further clarify whether changes in respiratory patterns detected through BVS could help identify patients at risk of COPD exacerbation or cardiac decompensation in OHS [16,17].
The main issues identified through BVS analysis are associated with clinically relevant outcomes. Adequate adherence to NIV, particularly use for at least 4h/day, has been linked to improved prognosis and clinical outcomes [18]. Unintentional leaks may compromise the effectiveness of therapy and contribute to discomfort, sleep disruption, PVA, and poor control of nocturnal hypoventilation [10]. In patients with ALS, upper airway obstruction occurring during NIV has been associated with poorer prognosis, even in the absence of oxygen desaturation [19]. Although the clinical significance of PVA remains debated, several studies suggest that it may negatively affect patient comfort, health-related quality of life, and sleep quality, all of which are particularly important in the setting of long-term NIV [20,21].
Although still limited, emerging data also suggests that implementing BVS data in long term NIV monitoring may improve clinically relevant outcomes. Rabec et al. demonstrated that combining BVS data with nocturnal oximetry reduced the majority of residual nocturnal respiratory events [13]. Ventilator data downloads may also facilitate optimization of domiciliary NIV delivery by enabling early and objective assessment of ventilator settings and unintentional leaks, thereby supporting outpatient NIV initiation and follow-up [14,22]. Finally, a recent study reported that the use of BVS was associated with improved survival and provided valuable prognostic information in patients with amyotrophic lateral sclerosis receiving home mechanical ventilation [23].
To date, long-term home NIV is probably one of the therapies benefiting from the most precise, easily accessible, and freely available follow-up data through BVS. Systematic use of these data could decrease the requirement for examinations such as arterial blood gas, oximetry, polysomnography, thus reducing the burden on patients and caregivers. Of course, randomized controlled trials are awaited to demonstrate, with a high level of evidence, the value of this monitoring [24]. However, the evidence already available in favor of this surveillance, as outlined above, versus its constraints and cost, strongly supports a wider implementation of this practice.
CON: “don’t put the cart before the horse” – the need for more evidence and understanding before incorporating NIV software data into clinical decision makingThe increase in prescribing of home non-invasive ventilation has been driven by evidence that this technology improves important outcomes including symptoms, hospital admissions and mortality [18,25–28]. The improvement in ventilator technology has supported the increase in home use with smaller, lighter devices; improved user interfaces; advanced titrating modes and more recently increased data derived from ventilator performance. Expansion of available tools for monitoring of home NIV has led to a recent ERS task force to address the issue of telemonitoring in home ventilation indicating the importance of this area and the acknowledgement that it is already used within clinical practice [29]. However, it is noteworthy that the recommendations of this guideline are all of very low certainty of evidence with some questions not answered due to the lack of available evidence [29].
Home NIV adherence is an important outcome to target in the management of chronic respiratory failure as there is an associated with improved patient outcomes and has often been the primary ventilator derived data used in clinical practice [9]. Data from home NIV devices now extends much beyond simple usage providing the clinician with information on leaks, residual apnoea level and even granularity of single night flow data to identify patient ventilator asynchronies. While access to these data is intuitively of appeal, the evidence that they can be consistently and accurately reviewed by clinicians to improve patient outcomes and that this can be achieved in an economical manner is lacking [29].
The cost of running a home ventilation programme is important with a clear relationship between country wealth and home ventilator prescriptions indicating that cost is a factor in limiting access to this intervention [30]. Even in developed health systems with current access to established HMV programmes, there is an increasing expansion of cost of healthcare that requires interventions to be reviewed to ensure they not only improve patient outcomes but also can be affordably delivered (www.oecd.org/en/publications/fiscal-sustainability-of-health-systems_9789264233386-en.html). It is important therefore that the newly available data from home NIV devices are fully assessed with the added value of the individual components understood prior to incorporating into routine clinical practice.
Evaluating complex interventions such as the use of ventilator data requires clear and robust methodology [31]. It is clear that not all ventilators provide the same data, furthermore the reliability of those data to accurately report the stated outcome is not consistent [32]. There are no clear industry standards to ensure that clinicians can review data confidently to allow interpretation and thus influence clinical management. For example, the accuracy of tidal volume measurements estimated by ventilator software is not consistently reported and when this is available it is often based on lung models and not validated in patients [33]. Previous bench studies from NIV devices have shown that even simple parameters such as delivered pressure may not be always consistent across different devices [34]. There is evidence that difference in performance in these bench tests does translate to clinically meaningful changes in NIV efficacy such as respiratory muscle unloading [35]. The limited data available in this area should therefore be carefully evaluated prior to incorporating into clinical practice guidelines. For example, while there is evidence that air leaks are associated with worse outcomes in NIV, the study evaluating this used two separate additional pneumotachographs placed into the ventilator circuit to measure inspiratory and expiratory volumes and thus allow an estimate of leak volume [10]. Whereas the data demonstrating the ventilator device leak estimation is accurate in patients using home NIV are lacking with factors such as unintentional leak and device type significantly impacting on reliability of data [36].
Much of the reported data in this area are from non-randomised or non-controlled trials [7,23,37] and so while building support for this intervention they are not compelling. There have been recent high-quality publications in this area with Prigent et al. reporting the results of a randomised clinical trial comparing telemonitoring remote support to usual care in patients newly established on home NIV [38]. The study utilised an established algorithm to review and respond to NIV device data during the 12 months follow-up period. While the primary outcome showed no difference between the groups there was evidence of improved ventilator compliance in the telemonitoring intervention group. However, as with all secondary outcome the results must be viewed with caution and have further validation. Furthermore, the study does not provide clarity on which aspects of the telemonitoring programme are responsible for any improvements in outcome. Is the NIV device data needed for this to be achieved, or could this be managed with closer clinician led follow up? The study also did not address the cost of establishing the telemonitoring or the additional interventions required.
In summary we should not let the excitement of new technology lead us away from the core clinical assessment needed for patients on home NIV, otherwise we may be reducing important interactions without the clear evidence that these face-to-face reviews can be safely replaced.
ConclusionThe integration of BVS into long-term home NIV follow-up represents a major evolution in respiratory care, providing clinicians with accessible, longitudinal, and real-time information on adherence, leaks, respiratory events, and patient–ventilator interactions. These tools offer the opportunity to optimize ventilator settings, identify at-risk situations early, facilitate outpatient management, and potentially reduce the burden of repeated investigations for both patients and caregivers. Emerging evidence further suggests that BVS-guided monitoring may improve ventilation quality and could positively influence clinically relevant outcomes in selected populations.
However, despite their intuitive appeal and growing integration into clinical practice, variability in reporting methods, differences between manufacturers, and the limitations of certain proprietary algorithms continue to complicate interpretation and contribute to heterogeneous practices across centers and countries. Importantly, BVS data should not be considered as direct surrogates for clinical outcomes, but rather tools to detect potential abnormalities and guide diagnostic strategies. Ultimately, whatever monitoring strategy is adopted, correlation with patient outcomes remains essential [39].
Future developments should focus on standardizing and expanding BVS capabilities to improve monitoring precision and bring software analysis closer to poly(somno)graphic assessment [40] but without ever forgetting that the rapid pace of technological innovation and the increasing availability of data should not make us forget the requirement for a rigorous demonstration of their clinical relevance and benefit.
Declaration of generative AI and AI-assisted technologies in the writing processAI tools (ChatGPT) have been used to improve the English writing of the PRO section, but no generative AI was used without supervision to produce content. After using this service, the author(s) reviewed and edited the content as needed and take(s) full responsibility for the content of the published article.
Conflict of interestsThe authors state that they have no conflict of interests. AL reports consulting fees from Air Liquide Medical Systems and lecturing fees from SOS Oxygène, Oxylis and Lowenstein Medical, outside the submitted work.








