



Patients undergoing solid-organ transplantation typically require long-term immunosuppressive therapy, increasing their risk of infections and tumour development. Epstein-Barr virus (EBV) is commonly associated with lymphoproliferative diseases [1]. However, isolated cases have described EBV-related smooth muscle tumours [2].
We present a 39-year-old female who underwent bilateral lung transplantation in May 2008 for cystic fibrosis. She tested seronegative for cytomegalovirus (CMV) and EBV in 2009 and subsequently seroconverted to positive EBV in 2015(viral load <125IU/mL in 2018). The donor tested positive for previous infections with CMV and EBV. Notable complications after transplantation included chronic bronchiolitis obliterans-type rejection 0-p in 2009 progressing to grade 1 in 2014, two episodes of grade A2 acute cellular rejection in 2010 and 2024, successfully treated with corticosteroid boluses.
In addition, the patient was diagnosed with chronic kidney disease in November 2009(serum creatinine 1.8mg/dL). However, creatinine levels remained between 1 and 2mg/dL until 2023, when they increased to 2–3mg/dL. Pronounced deterioration occurred in August 2024, with creatinine levels rising to 4–5mg/dL, leading to the need for dialysis initiation. This coincided with an episode of acute rejection and respiratory infection requiring corticosteroid therapy and antibiotic.
She was maintained on immunosuppressive therapy with tacrolimus until 2009, when an episode of haemolytic uremic syndrome occurred. Tacrolimus was initially replaced with everolimus; however, due to the inability to achieve adequate immunosuppressive levels, a combination of both drugs was subsequently introduced. Since then, drug levels remained stable, with tacrolimus between 5 and 10ng/mL and everolimus between 3 and 6ng/mL.
From a respiratory standpoint, the patient never required home oxygen therapy, consistently maintaining oxygen saturation levels around 97–98%. In pulmonary function tests, during the first year following transplantation, FEV1 was around 2.8L (101%) and FVC around 3L (94%). In 2009, FEV1 fell to 2.5L and FVC to 2.7L, with a progressive decline of FEV1 to 2.1L (76%) by 2024, whilst FVC remained at 2.7L.
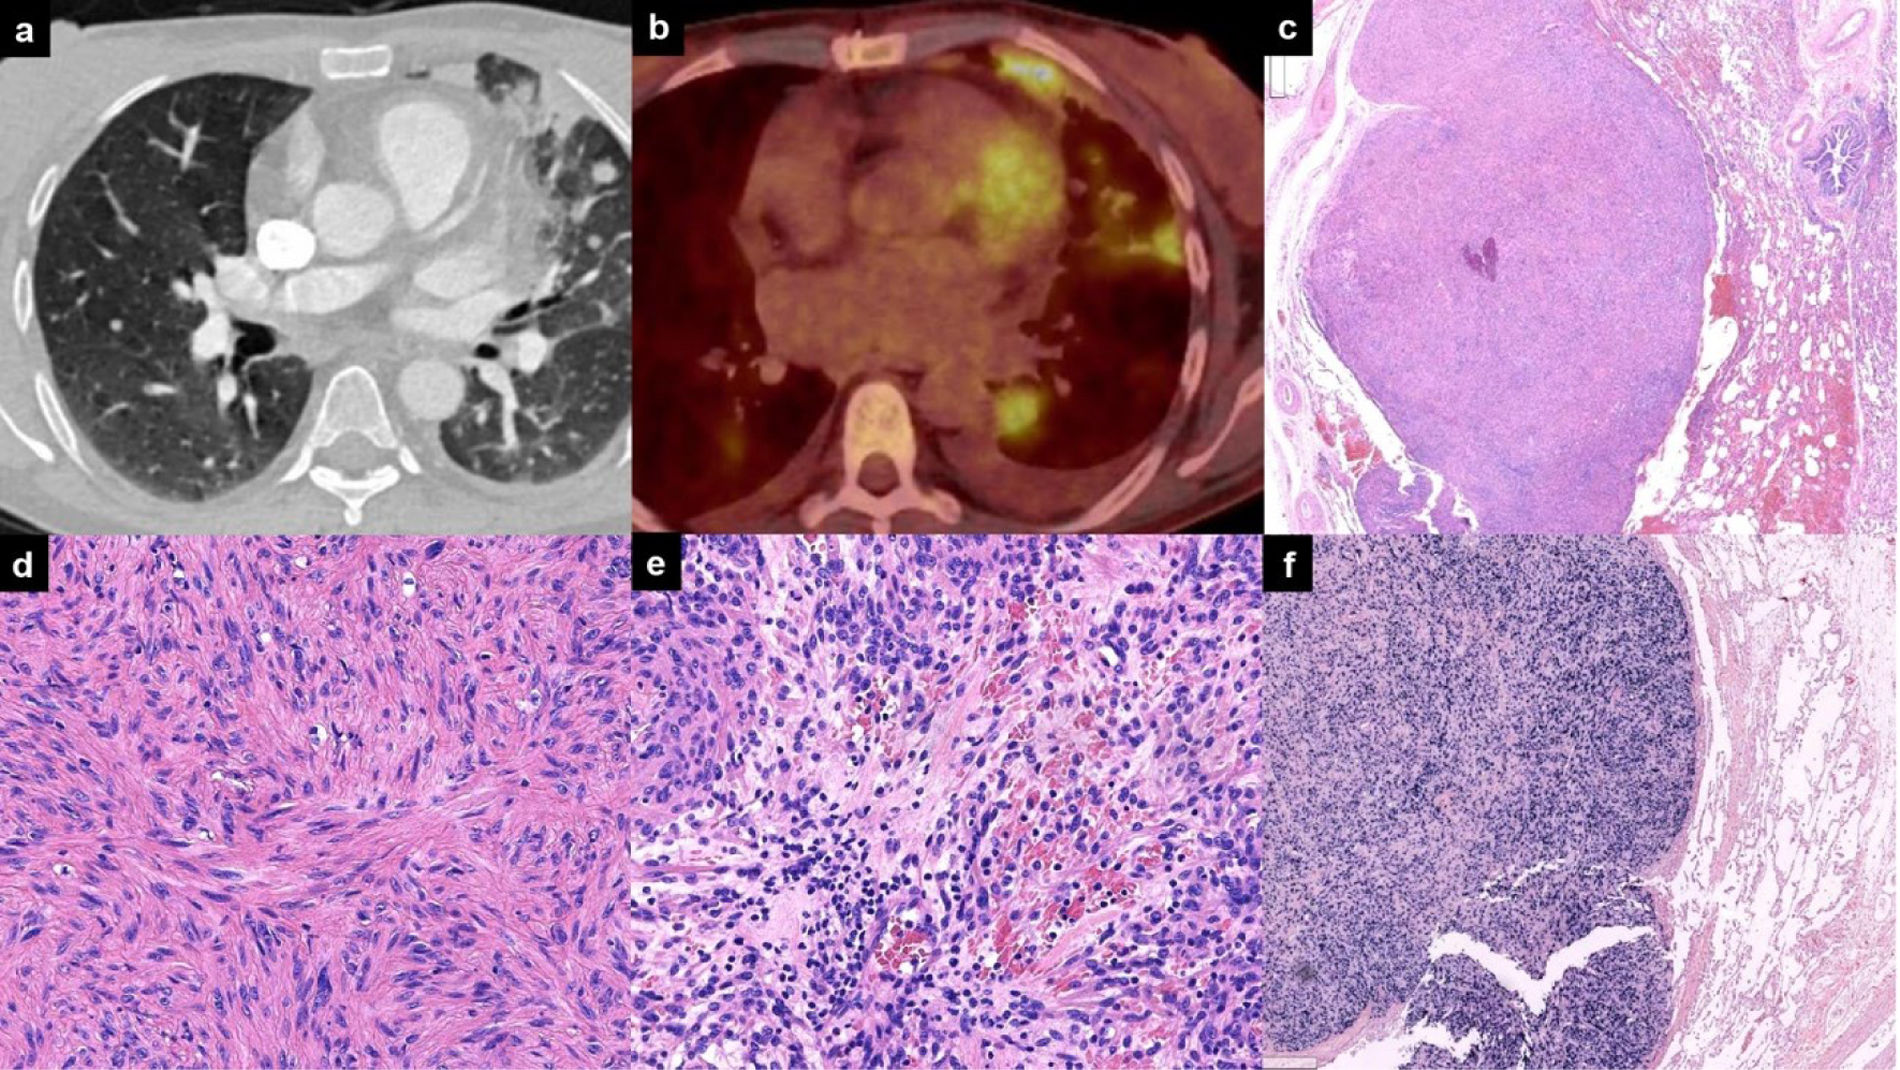
In a routine chest X-ray, bilateral patchy opacities of likely infectious or inflammatory origin were identified, prompting a computed-tomography (CT) scan in November 2023. The CT revealed bilateral lung involvement, with multiple well-defined pulmonary nodules randomly distributed, the largest measuring 1cm in the lingula (Fig. 1a). A subsequent positron emission tomography (PET) showed pathological uptake in the nodules, with no significant lymphadenopathy or extrapulmonary lesions (Fig. 1b). The patient was clinically stable from a respiratory standpoint, eupneic at rest with 95–97% oxygen saturation and maintaining an active lifestyle. She denied constitutional symptoms or any other complaints.

(a) CT scan showing multiple bilateral nodules; (b) PET-CT scan showing multiple nodules in the left lung with pathological uptake; (c–e) histological section at different magnifications, stained with haematoxylin–eosin, showing a pulmonary nodule with spindle-cell morphology and venous vascular localization at the level of the bronchovascular bundles; (f) EBER ISH staining.
Initial fine-needle aspiration biopsy (FNAB) failed to yield diagnostic material, showing no cytological evidence of malignancy. Given the suspicion of a fungal infection and a bronchoalveolar lavage positive for Cryptococcus diffluens, treatment with isavuconazole was initiated in February 2024.
However, follow-up imaging in August 2024 showed no improvement. She was referred to thoracic surgery for further evaluation. In October 2024, wedge resection of the lingular segment was performed including several of the described nodules. The surgery proceeded without complications, however, due to worsening of the renal function, the patient required adjustments in her usual diuretic regimen. Finally, she was discharged on postoperative day nine.
Histopathological analysis revealed multiple spindle cell morphology pulmonary nodules with venous vascular localization along bronchovascular bundles (Fig. 1c–e). Epstein-Barr encoding region in situ hybridization (EBER ISH) showed diffuse EBV positivity in the smooth muscle proliferation (Fig. 1f).
EBV-associated smooth muscle tumours are rare and poorly understood. Some reports suggest a donor-recipient mismatch (EBV-positive donor, EBV-negative recipient) may be a factor, although this remains unproven [2]. These tumours can manifest in any organ of the recipient, not only in the transplanted one [3,4]. The reduction in cytotoxic T cells caused by immunosuppressive treatment promotes the uncontrolled proliferation of B cells infected with EBV. A reduction in immunosuppression levels would enable an immune response against tumour cells and EBV, whilst acknowledging the increased risk of graft rejection [4]. EBV is capable of evading immune surveillance during its latent phase, remaining undetected and being able to activate the PI3K/Akt intracellular pathway, which is involved in smooth muscle cell proliferation and commonly present in cancer cells. Furthermore, mTOR is typically overexpressed in these patients, acting as substrate for the activation of PI3K/Akt intracellular pathway. For this reason, longer survival is reported in patients who received surgical treatment and mTOR inhibitors therapy rather than cyclosporine [5,6].
However, there is no standardised treatment. In multifocal cases such as this, chemotherapy may be considered due to the limited feasibility of complete surgical resection [7]. In this case, the patient underwent surgery October 2024. The histopathological report was obtained on November 2024, and the patient was admitted at the end of November 2024 due to fever and worsening renal function, eventually passing away on 17 December 2024. The short interval between the diagnosis and the patient's clinical deterioration made it difficult to modify the immunosuppressive treatment. Cardiac tamponade was attributed to acute renal failure superimposed on chronic kidney disease. Furthermore, thrombotic microangiopathy may also have been a contributing factor, initially favoured by high doses of tacrolimus and subsequently by the combination of calcineurin inhibitors and mTOR inhibitors. Further research is needed to define optimal management strategies for this rare entity.
Declaration of generative AI and AI-assisted technologies in the writing processArtificial intelligence was employed exclusively to assist in the translation of select sections of the manuscript.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Conflicts of interestThe authors declare not to have any conflicts of interest that may be considered to influence directly or indirectly the content of the manuscript.








