






Idiopathic pulmonary fibrosis (IPF) predominantly affects older adults. Frailty is increasingly recognized as an important feature of IPF, although its prognostic value remains uncertain. This study aimed to assess the prevalence of frailty and concordance among validated instruments, characterize the principal domains of vulnerability identified through comprehensive geriatric assessment (CGA), and evaluate the prognostic value of integrating frailty with indices of respiratory disease severity in older adults with IPF.
MethodsWe conducted a prospective, single-center study of patients aged 65 years or older with confirmed IPF. Frailty was assessed using the Fried frailty phenotype (FFP), a CGA-derived Frailty Index (CGA-FI), and the Clinical Frailty Scale (CFS). The primary outcome was a composite of all-cause mortality or acute exacerbation during follow-up. Cox proportional hazards models and bootstrap-derived concordance indices were used to evaluate prognostic associations and model discrimination.
ResultsAmong the 140 patients included, the prevalence of frailty ranged from 16.4% according to the CGA-FI to 22.3% according to the FFP, whereas 19.3% were classified as frail according to the CFS. During a median follow-up of 465 days (IQR, 221–1076 days), 35 patients (25.0%) experienced the composite outcome. Frailty assessed using the CFS (CFS ≥5: HR, 3.94; 95%CI, 1.81–8.58) and a higher Gender-Age-Physiology (GAP) stage (GAP II–III: HR, 3.11; 95%CI, 1.39–7.00) were independently associated with the composite outcome. The integrated GAP-CFS model showed good discrimination, with a bootstrap-derived Harrell C index of 0.72 (95%CI, 0.62–0.81). Patients who experienced events also had higher Strength, Assistance in Walking, Rising From a Chair, Climbing Stairs, and Falls (SARC-F) scores and greater functional impairment.
ConclusionsFrailty is common and clinically relevant in IPF. Integrating frailty measures with pulmonary indices improves prognostic stratification and supports the use of the CFS and CGA to guide personalized, multidimensional care.

Idiopathic pulmonary fibrosis (IPF) is a chronic fibrosing interstitial pneumonia of unknown origin characterized by progressive deterioration in lung function, worsening dyspnea, persistent cough, impaired quality of life, and poor prognosis [1]. The disease primarily affects older adults, with a median age at diagnosis of approximately 65 years [2]. Aging contributes to the pathogenesis of IPF by promoting epithelial senescence through oxidative stress, telomere attrition, and extracellular matrix remodeling, making IPF a clinical model of accelerated biological aging [3].
Frailty, defined as a state of reduced physiological reserve and increased vulnerability to stressors that can lead to adverse outcomes such as disability, delirium, or death, may represent the clinical expression of this accelerated aging [4,5].
A recent systematic review by Verduri et al. highlighted the high prevalence of frailty across interstitial lung diseases and its consistent association with adverse clinical outcomes. The review also emphasized the need to develop and implement standardized methods for frailty assessment [6]. Despite its recognized clinical relevance and substantial prevalence among individuals with IPF [7–12], systematic frailty assessment is rarely incorporated into routine care.
Furthermore, frailty in IPF has typically been assessed using a single instrument, such as the Frailty Index [9,11], Fried phenotype [7,10], or Clinical Frailty Scale [8]. However, concordance among these approaches is known to be limited [13], and the optimal instrument for this population remains uncertain. Notably, no previous study has systematically incorporated a comprehensive geriatric assessment (CGA) [14], a multidimensional evaluation of physical, cognitive, nutritional, psychological, and social domains. CGA provides an opportunity to identify individual profiles of vulnerability and support personalized care pathways encompassing disease-modifying treatments, supportive interventions, and timely integration of palliative care [12].
This study aimed to assess frailty in older adults with IPF using multiple validated instruments, apply CGA to characterize multidimensional vulnerability, and develop an integrated prognostic model combining pulmonary function and frailty measures to improve short-term risk prediction.
MethodsStudy design, data collection, and ethics statementWe conducted a prospective, single-center, observational study involving consecutive adults aged 65 years or older with IPF who were referred to the tertiary IPF clinic at Fondazione IRCCS San Gerardo dei Tintori (Monza, Italy). IPF was diagnosed according to international guidelines [1].
All participants gave their prior written informed consent and underwent systematic collection of biological, sociodemographic, and clinical data at baseline and at the 6-month follow-up assessment. The study was conducted in accordance with the Declaration of Helsinki, was approved by the institutional review board of Fondazione IRCCS San Gerardo dei Tintori on May 23, 2024 (approval No. 546), and was reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement.
Integrated pulmonology-geriatric outpatient protocolPatients were jointly assessed by the pulmonology and geriatrics teams according to a shared institutional protocol. The clinical team comprised a pulmonologist, a geriatrician or trained resident with expertise in CGA, and a dedicated nurse. The geriatric component of the outpatient assessment was conducted by clinicians with established expertise in frailty evaluation and CGA. All physicians received training in the administration of CGA and frailty instruments to ensure consistency and reproducibility.
The assessment followed a 2-step approach, with both components completed on the same day. First, the pulmonologist conducted a comprehensive respiratory assessment using standardized procedures. This was followed by the CGA performed by the geriatrics team.
Baseline clinical variablesThe pulmonology assessment included a detailed clinical evaluation, pulmonary function tests, and the 6-minute walk test, all performed according to international guidelines [15,16]. Forced vital capacity (FVC) and total lung capacity (TLC) were recorded, and the best values from at least 3 technically acceptable maneuvers were retained for analysis. Diffusing capacity of the lungs for carbon monoxide (DLCO) was measured using the single-breath technique.
FVC and DLCO, together with age and sex, were used to calculate the Gender-Age-Physiology (GAP) index, a validated multidimensional staging system for assessing disease severity and mortality risk in IPF [17]. The GAP index stratifies patients into 3 stages, I through III, corresponding to increasing disease severity and poorer survival.
Moreover, a CGA was performed for all patients. Comorbidity burden was assessed using the Charlson Comorbidity Index. Functional status was evaluated using the Activities of Daily Living scale [18] and Instrumental Activities of Daily Living scale [19]. Nutritional status was assessed using the Mini Nutritional Assessment-Short Form [20], with scores of 7 or lower indicating malnutrition.
Muscle strength was evaluated using standardized handgrip dynamometry; values below 27kg in men and 16kg in women were considered indicative of dynapenia [21]. Physical performance was measured using the Short Physical Performance Battery [22], which comprises balance, gait-speed, and repeated chair-stand tests. Cognitive function was assessed using the Montreal Cognitive Assessment [23], with Italian normative thresholds applied to define cognitive impairment [24].
Frailty assessmentFrailty was assessed using 3 validated instruments: the Fried frailty phenotype [25], the Frailty Index derived from the CGA [5], and the Clinical Frailty Scale [26].
Frailty according to the Fried phenotype was assessed across 5 domains: unintentional weight loss, exhaustion, low physical activity, slow gait speed, and reduced muscle strength. Weight loss was defined as a loss of more than 4.5kg or more than 5% of body weight during the previous year. Exhaustion was identified using 2 items from the Center for Epidemiologic Studies Depression Scale [27]. Gait speed was measured over 4.5m at the patient's usual pace and classified using sex- and height-specific cutoffs. Muscle strength was assessed using handgrip dynamometry and sex-specific thresholds. Physical activity was evaluated using the Physical Activity Scale for the Elderly [28], with scores below established cutoffs classified as low. Participants meeting ≥3 of the 5 criteria were classified as frail.
The CGA-FI was constructed using 43 items encompassing multiple geriatric domains, including comorbidity, cognition, mood, functional status, sensory impairment, and nutrition (Supplementary Table 1). Each deficit was coded as 1 when present and 0 when absent. The sum of the deficits was divided by the total number of items assessed to generate a continuous score ranging from 0 to 1. A cutoff of 0.25 or higher was used to classify participants as frail, consistent with former studies [29,30].
The CFS was rated by trained investigators using a standardized 9-point pictorial and descriptive scale supported by a classification tree to minimize subjectivity [13]. Patients with scores ranging from 5 to 9 were categorized as frail, consistent with thresholds established in previous studies [4].
Follow-up and outcome variableAll patients were followed from the date of the baseline assessment until the occurrence of the outcome of interest or the end of the available follow-up period on May 31, 2025. The median follow-up duration was 465 days (IQR, 221–1076 days).
The primary endpoint was the time to a composite of all-cause mortality or acute exacerbation of IPF, whichever occurred first. The composite end point was selected on the basis of both clinical relevance and the need to ensure a sufficient number of events. This approach improved statistical power by encompassing the 2 most clinically important adverse outcomes in IPF during the limited follow-up period.
For patients who experienced both an acute exacerbation and subsequent death during follow-up, only the first event was considered in the composite end point analysis. Vital status and date of death were obtained through the Lombardy Regional Socio-Healthcare Information System for all participants, including those who did not attend follow-up visits.
Acute exacerbation was defined according to international criteria as an acute, clinically significant respiratory deterioration characterized by new, widespread alveolar abnormalities [31]. Diagnostic criteria included a previous or concurrent diagnosis of IPF; acute worsening or development of dyspnea within 1 month; new bilateral ground-glass opacities, consolidations, or both on computed tomography superimposed on a usual interstitial pneumonia pattern; and deterioration not fully explained by cardiac failure or fluid overload.
Statistical analysisContinuous variables are expressed as mean (SD) or median (IQR), as appropriate, and categorical variables as frequencies and percentages. Between-group differences were assessed using the independent-samples t test, Wilcoxon rank-sum test, chi-square test, or Fisher exact test, as appropriate.
Agreement among frailty measures was assessed using Kendall coefficient of concordance, and their discriminative ability was evaluated using concordance indices.
Given the limited number of events and to minimize the risk of overfitting, a clinically driven prognostic model was developed by integrating the GAP index with the CFS. Cox proportional hazards regression models were used to evaluate the associations of GAP stage and CFS category with time-to-event outcomes.
Internal validation of model performance was performed using 1000 bootstrap samples. Harrell C index was calculated for each model. The median of the distribution of discrimination estimates was reported as the final estimate, with the 2.5th and 97.5th percentiles used to derive the bootstrap 95%CI.
To assess the potential effect of competing risks on HR estimates for acute exacerbation, a sensitivity analysis was performed using the Fine-Gray subdistribution hazards model [32].
All analyses were performed using SAS, version 9.4 (SAS Institute Inc). All tests were 2-sided, and a P value less than .05 was considered statistically significant.
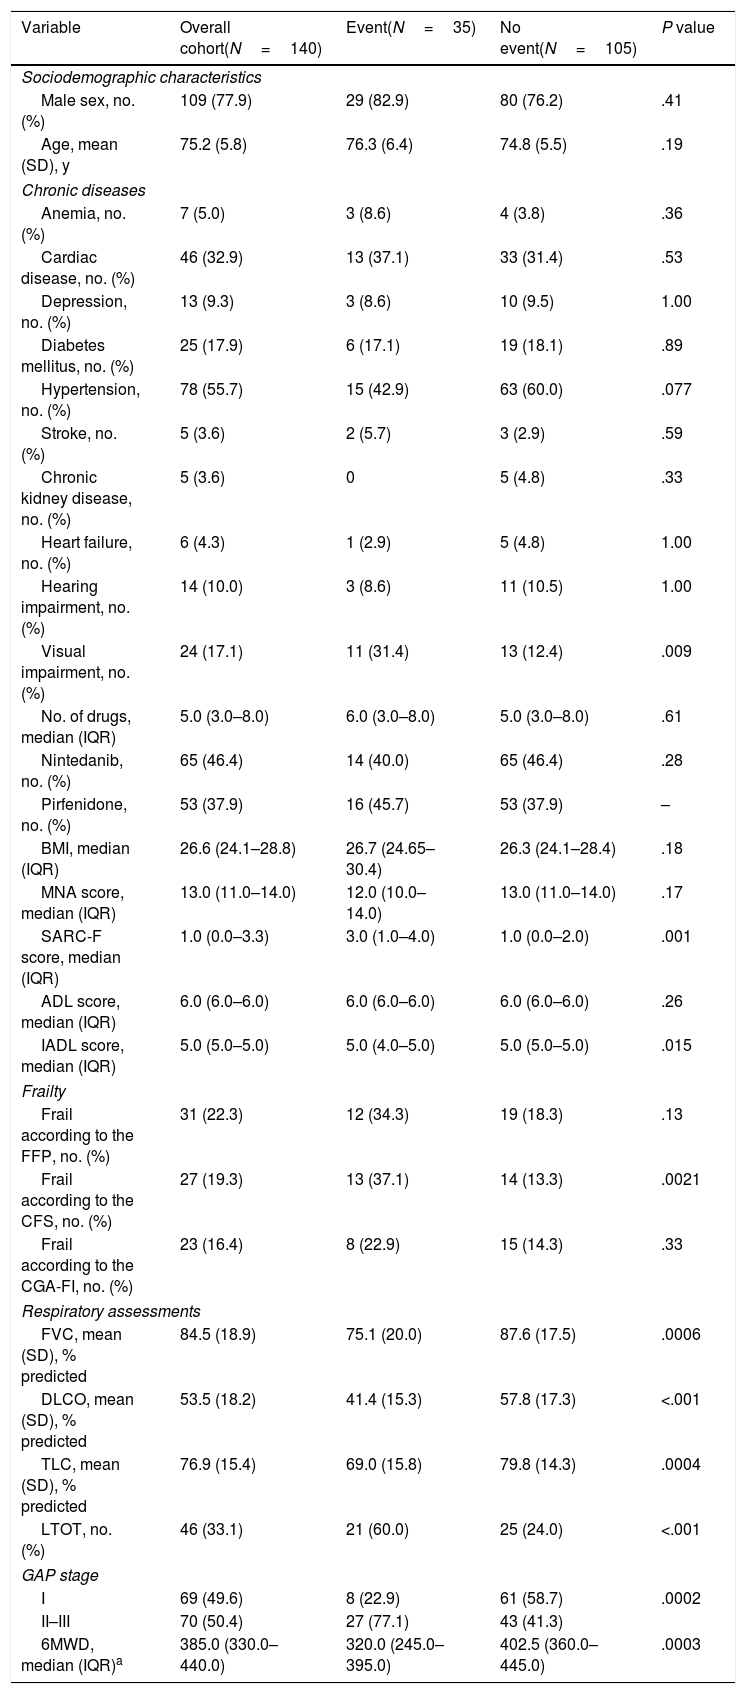
ResultsWe enrolled a total of 140 consecutive patients with IPF. Baseline characteristics are summarized in Table 1.
Baseline characteristics of the study population.
| Variable | Overall cohort(N=140) | Event(N=35) | No event(N=105) | P value |
|---|---|---|---|---|
| Sociodemographic characteristics | ||||
| Male sex, no. (%) | 109 (77.9) | 29 (82.9) | 80 (76.2) | .41 |
| Age, mean (SD), y | 75.2 (5.8) | 76.3 (6.4) | 74.8 (5.5) | .19 |
| Chronic diseases | ||||
| Anemia, no. (%) | 7 (5.0) | 3 (8.6) | 4 (3.8) | .36 |
| Cardiac disease, no. (%) | 46 (32.9) | 13 (37.1) | 33 (31.4) | .53 |
| Depression, no. (%) | 13 (9.3) | 3 (8.6) | 10 (9.5) | 1.00 |
| Diabetes mellitus, no. (%) | 25 (17.9) | 6 (17.1) | 19 (18.1) | .89 |
| Hypertension, no. (%) | 78 (55.7) | 15 (42.9) | 63 (60.0) | .077 |
| Stroke, no. (%) | 5 (3.6) | 2 (5.7) | 3 (2.9) | .59 |
| Chronic kidney disease, no. (%) | 5 (3.6) | 0 | 5 (4.8) | .33 |
| Heart failure, no. (%) | 6 (4.3) | 1 (2.9) | 5 (4.8) | 1.00 |
| Hearing impairment, no. (%) | 14 (10.0) | 3 (8.6) | 11 (10.5) | 1.00 |
| Visual impairment, no. (%) | 24 (17.1) | 11 (31.4) | 13 (12.4) | .009 |
| No. of drugs, median (IQR) | 5.0 (3.0–8.0) | 6.0 (3.0–8.0) | 5.0 (3.0–8.0) | .61 |
| Nintedanib, no. (%) | 65 (46.4) | 14 (40.0) | 65 (46.4) | .28 |
| Pirfenidone, no. (%) | 53 (37.9) | 16 (45.7) | 53 (37.9) | – |
| BMI, median (IQR) | 26.6 (24.1–28.8) | 26.7 (24.65–30.4) | 26.3 (24.1–28.4) | .18 |
| MNA score, median (IQR) | 13.0 (11.0–14.0) | 12.0 (10.0–14.0) | 13.0 (11.0–14.0) | .17 |
| SARC-F score, median (IQR) | 1.0 (0.0–3.3) | 3.0 (1.0–4.0) | 1.0 (0.0–2.0) | .001 |
| ADL score, median (IQR) | 6.0 (6.0–6.0) | 6.0 (6.0–6.0) | 6.0 (6.0–6.0) | .26 |
| IADL score, median (IQR) | 5.0 (5.0–5.0) | 5.0 (4.0–5.0) | 5.0 (5.0–5.0) | .015 |
| Frailty | ||||
| Frail according to the FFP, no. (%) | 31 (22.3) | 12 (34.3) | 19 (18.3) | .13 |
| Frail according to the CFS, no. (%) | 27 (19.3) | 13 (37.1) | 14 (13.3) | .0021 |
| Frail according to the CGA-FI, no. (%) | 23 (16.4) | 8 (22.9) | 15 (14.3) | .33 |
| Respiratory assessments | ||||
| FVC, mean (SD), % predicted | 84.5 (18.9) | 75.1 (20.0) | 87.6 (17.5) | .0006 |
| DLCO, mean (SD), % predicted | 53.5 (18.2) | 41.4 (15.3) | 57.8 (17.3) | <.001 |
| TLC, mean (SD), % predicted | 76.9 (15.4) | 69.0 (15.8) | 79.8 (14.3) | .0004 |
| LTOT, no. (%) | 46 (33.1) | 21 (60.0) | 25 (24.0) | <.001 |
| GAP stage | ||||
| I | 69 (49.6) | 8 (22.9) | 61 (58.7) | .0002 |
| II–III | 70 (50.4) | 27 (77.1) | 43 (41.3) | |
| 6MWD, median (IQR)a | 385.0 (330.0–440.0) | 320.0 (245.0–395.0) | 402.5 (360.0–445.0) | .0003 |
ADL, activities of daily living; BMI, body mass index; CFS, Clinical Frailty Scale; CGA-FI, comprehensive geriatric assessment-Frailty Index; DLCO, diffusing capacity of the lungs for carbon monoxide; FFP, Fried frailty phenotype; FVC, forced vital capacity; GAP, Gender-Age-Physiology; IADL, instrumental activities of daily living; IQR, interquartile range; LTOT, long-term oxygen therapy; MNA, Mini Nutritional Assessment; SARC-F, Strength, Assistance in Walking, Rising From a Chair, Climbing Stairs, and Falls; SD, standard deviation; TLC, total lung capacity; 6MWD, 6-minute walk distance.
The mean age of the overall cohort was 75.2 years (SD, 5.8 years), and 109 patients (77.9%) were men. Comorbidities were common, including cardiac disease in 46 patients (32.9%), diabetes in 25 (17.9%), and hypertension in 78 (55.7%). Visual impairment was present in 24 patients (17.1%), and hearing impairment in 14 (10.0%). The median number of drugs was 5 (IQR, 3–8). Indicators of biological vulnerability included malnutrition in 17 patients (12.1%), dynapenia in 31 (22.1%), and impaired physical performance, defined as a Short Physical Performance Battery (SPPB) score <10, in 47 (33.8%). Cognitive impairment was identified in 34 patients (24.3%), depressive symptoms in 13 (9.3%), and limitations in instrumental activities of daily living (IADL) in 31 (22.1%). The prevalence of frailty varied according to the instrument used, ranging from 23 patients (16.4%) according to the CGA-FI to 27 (19.3%) according to the CFS and 31 (22.3%) according to the Fried frailty phenotype (Fig. 1).

During a median follow-up of 465 days (IQR, 221–1076 days), a total of 35 patients experienced the composite outcome. Of these, 8 experienced an acute exacerbation without subsequent death, 14 died without a previous acute exacerbation, and 13 experienced both an acute exacerbation and subsequent death.
Patients who experienced the composite endpoint had a greater degree of multidimensional vulnerability than those who did not experience an event. In particular, they had a higher risk of sarcopenia, as assessed using the SARC-F questionnaire (median score, 3.0 [IQR, 1.0–4.0] vs 1.0 [IQR, 0.0–2.0]; P=.001), greater dependence in instrumental activities of daily living (median IADL score, 5.0 [IQR, 4.0–5.0] vs 5.0 [IQR, 5.0–5.0]; P=.015), and a higher prevalence of frailty according to the CFS (37.1% vs 13.3%; P=.002).
Patients who experienced an event also had lower mean percent-predicted FVC (75.1% [SD, 20.0%] vs 87.6% [SD, 17.5%]; P=.0006), DLCO (41.4% [SD, 15.3%] vs 57.8% [SD, 17.3%]; P<.0001), and TLC (69.0% [SD, 15.8%] vs 79.8% [SD, 14.3%]; P=.0004). Long-term oxygen therapy was significantly more common in the event group (60.0% vs 24.0%; P<.0001). In addition, GAP stage II was more prevalent among patients who experienced events than among those who did not (27/35 [77.1%] vs 43/104 [41.3%]; P<.001). No significant differences in the distribution of antifibrotic treatment were observed according to outcome status.
Agreement among the 3 frailty measures – the CFS, FFP, and CGA-FI– was substantial (Kendall coefficient of concordance, 0.73; P<.0001).
Kaplan–Meier analyses showed significant differences in event-free survival according to both CFS category and GAP stage. Patients with a greater frailty burden and more advanced respiratory disease had poorer clinical trajectories for both the composite outcome and its individual components (Fig. 2).

Event-free survival according to frailty status and respiratory disease severity in older patients with idiopathic pulmonary fibrosis. Kaplan–Meier curves showing the associations of Clinical Frailty Scale (CFS) categories and Gender-Age-Physiology (GAP) stage with clinical outcomes during follow-up. Panels A through C show survival curves according to CFS category – robust (CFS scores 1–3), prefrail (CFS score 4), and frail (CFS score ≥5) – for the composite outcome, all-cause mortality, and acute exacerbation, respectively. Panels D through F show the corresponding analyses according to GAP stage, comparing stage I with stages II to III. Differences among groups were assessed using the log-rank test.
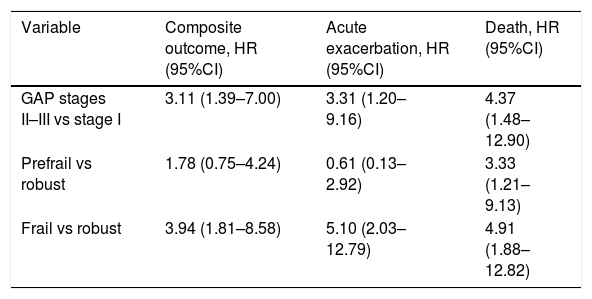
In Cox proportional hazards models including GAP stage and CFS category, both variables were associated with clinical outcomes (Table 2). Compared with GAP stage I, GAP stages II to III were associated with a higher risk of the composite outcome (HR, 3.11; 95%CI, 1.39–7.00), acute exacerbation (HR, 3.31; 95%CI, 1.20–9.16), and mortality (HR, 4.37; 95%CI, 1.48–12.90). Compared with robust patients, those classified as frail according to the CFS had a higher risk of the composite outcome (HR, 3.94; 95%CI, 1.81–8.58), acute exacerbation (HR, 5.10; 95%CI, 2.03–12.79), and mortality (HR, 4.91; 95%CI, 1.88–12.82). Patients classified as prefrail (CFS score of 4) also had a higher risk of mortality (HR, 3.33; 95%CI, 1.21–9.13). Competing-risk analysis using the Fine-Gray model for acute exacerbation yielded consistent results.
Multivariable HRs for Clinical Frailty Scale category and Gender-Age-Physiology stage in relation to the composite outcome, acute exacerbation, and death.
| Variable | Composite outcome, HR (95%CI) | Acute exacerbation, HR (95%CI) | Death, HR (95%CI) |
|---|---|---|---|
| GAP stages II–III vs stage I | 3.11 (1.39–7.00) | 3.31 (1.20–9.16) | 4.37 (1.48–12.90) |
| Prefrail vs robust | 1.78 (0.75–4.24) | 0.61 (0.13–2.92) | 3.33 (1.21–9.13) |
| Frail vs robust | 3.94 (1.81–8.58) | 5.10 (2.03–12.79) | 4.91 (1.88–12.82) |
CFS, Clinical Frailty Scale; GAP, Gender-Age-Physiology; HR, hazard ratio; 95%CI, 95% confidence interval.
To further assess the prognostic information provided by integrating frailty and respiratory disease severity, model discrimination was evaluated using bootstrap-derived Harrell C indices. The model including the CFS alone yielded C indices of 0.67 (95%CI, 0.59–0.76) for the composite outcome, 0.72 (95%CI, 0.62–0.81) for mortality, and 0.71 (95%CI, 0.60–0.82) for acute exacerbation. After integration with the GAP index, the corresponding Harrell C indices were 0.72 (95%CI, 0.62–0.81), 0.78 (95%CI, 0.69–0.87), and 0.77 (95%CI, 0.65–0.87), respectively.
DiscussionIn this prospective study of 140 patients with IPF, frailty was highly prevalent, affecting 16–22% of patients, depending on the assessment instrument used. Despite variation across instruments, concordance among frailty measures was substantial, suggesting that they capture overlapping, although not identical, dimensions of biological vulnerability. Among the instruments evaluated, the CFS showed the strongest prognostic value, with frail patients (CFS score ≥5) having an approximately 4-fold higher risk of the composite outcome during follow-up. Importantly, integrating the CFS with the GAP index yielded a clinically relevant prognostic framework that captured both respiratory disease severity and multidimensional vulnerability, thereby supporting a more comprehensive assessment of prognosis in patients with IPF.
Patients who experienced adverse outcomes had significantly greater respiratory impairment, including lower FVC, DLCO, and TLC values and a higher prevalence of long-term oxygen therapy. These findings reinforce the well-established importance of pulmonary function as a cornerstone of prognostic assessment in IPF. In addition, our results extend this perspective by showing that combining frailty assessment with the GAP index may further improve risk stratification because respiratory dysfunction and biological vulnerability appear to provide complementary prognostic information.
Another finding of interest was the progressive increase in risk across CFS categories. Although patients classified as frail had the highest risk of adverse outcomes, those classified as prefrail also had a higher risk of mortality. This association was not consistently observed for acute exacerbation or the composite outcome, possibly because of the limited number of events. Nevertheless, it suggests that declining physiological reserve may become clinically relevant before frailty is fully established. These findings support the assessment of frailty as a continuum of vulnerability rather than as a simple dichotomous classification in older adults with IPF.
Our results reinforce and extend the existing evidence regarding the clinical relevance of frailty in populations with interstitial lung disease. In a recent systematic review, Verduri et al. highlighted the high prevalence and prognostic relevance of frailty across chronic respiratory diseases while emphasizing the need for more standardized approaches to frailty assessment [6]. Our study extends these observations by directly comparing multiple frailty instruments in a homogeneous cohort of patients with IPF and by integrating frailty assessment with CGA and pulmonary disease severity indices.
In the study by Farooqi et al. [7], frailty assessed using the FFP was identified in 26% of patients with fibrotic interstitial lung disease, whereas 56% were classified as prefrail. Both groups were independently associated with higher mortality and hospitalization rates than nonfrail patients. Similarly, in a large multicenter cohort, Guler et al. [8] reported that 21% of patients with fibrotic interstitial lung disease were frail according to the CFS and that higher CFS scores independently predicted mortality. Our results are consistent with these findings, confirming the prognostic relevance of the CFS in a homogeneous population with IPF and supporting its incorporation into multidimensional assessment frameworks.
From a complementary perspective, Sheth et al. [10] investigated 50 older patients with IPF and found that 48% met the Fried criteria for frailty. Frailty was significantly associated with older age; lower FVC, forced expiratory volume in 1 second, and DLCO; shorter 6-minute walk distance; more severe dyspnea and fatigue; a greater number of comorbidities; and frequent geriatric conditions, including incontinence, sensory impairment, dizziness, falls, and functional limitations. Our study expands on these findings by adopting a CGA-based framework that provides a broader multidimensional characterization of vulnerability.
The incomplete concordance among instruments highlights the need for a more refined understanding of which measures most accurately capture vulnerability in IPF. The prognostic performance of the CFS may reflect its ability to integrate multiple domains of health status through an algorithm based on functional ability, including ADL and IADL, perceived health status, and comorbidity burden. This observation is consistent with the findings of Guler et al. [8] and further supports the prognostic validity of this instrument.
Beyond global frailty measures, our data suggest that specific domains of vulnerability – particularly those related to muscle and physical function – have substantial prognostic importance. Patients with adverse outcomes had higher SARC-F scores, indicating a greater risk of sarcopenia, and lower IADL scores, reflecting greater impairment in complex activities of daily living. Together, these findings indicate that frailty in IPF is not a uniform entity but rather a multidimensional state in which sarcopenia and impaired performance of complex daily activities may have a central role.
The association among frailty, musculoskeletal decline, and mortality has previously been explored by Sridhar et al. [9], who reported sarcopenia in 12.8% of patients, with a trend toward increased mortality, and by Faverio et al. [33], who observed sarcopenia in almost one-quarter of patients at the time of IPF diagnosis. In our cohort, reduced handgrip strength was present in 22% of patients, reinforcing the hypothesis that muscular impairment may represent one of the biological mechanisms linking frailty to an adverse prognosis in IPF.
The clinical implications of our findings are 2-fold. First, they support CGA as an important tool for assessing older adults with IPF. By systematically evaluating cognition, mood, nutrition, physical performance, and social support, CGA provides a multidimensional profile of vulnerability that extends beyond respiratory function. This information may guide individualized care strategies and support the early integration of coordinated palliative care. Second, our findings support the CFS as a practical and prognostically meaningful screening instrument for patients with IPF. Its simplicity and reproducibility make it particularly suitable for routine clinical practice and may allow it to serve as an entry point to a more comprehensive geriatric assessment.
Several limitations should be acknowledged. First, this was a single-center study, which may limit the generalizability of the findings. Second, frailty was assessed only at enrollment, irrespective of the interval between IPF diagnosis and study inclusion, precluding evaluation of longitudinal changes in frailty.
Frailty is increasingly recognized as a dynamic and potentially reversible condition. Targeted interventions – including pulmonary rehabilitation, nutritional optimization, comprehensive geriatric management, and, in selected patients, lung transplantation – may improve frailty status and clinical outcomes. Recent evidence from a systematic review and meta-analysis showing improvement in frailty after solid-organ transplantation further supports the concept that frailty should be considered a potentially modifiable therapeutic target [34,35].
In addition, patients were enrolled at different stages of IPF progression, and frailty may therefore have been influenced by disease duration and severity. Nevertheless, the consistent association between frailty and adverse outcomes across heterogeneous clinical profiles strengthens the robustness of our observations. Finally, although longitudinal outcome data were available and analyzed using time-to-event methods, external validation in larger multicenter cohorts with longer follow-up is required to confirm the generalizability of these findings.
ConclusionsFrailty is common and clinically relevant among older adults with IPF. Its assessment, particularly using the CFS, provides independent prognostic information beyond conventional respiratory indices. Incorporating frailty assessment into routine clinical pathways may improve risk stratification, support personalized and holistic care, and facilitate earlier supportive and palliative interventions, ultimately improving the quality and continuity of care in this vulnerable population.
Authors’ contributionsCO, GF, PF, FL, and GB were responsible for the study concept and design. CO, GF, IC, UZ, RG, AMO, EP, MCF, CT, LB, AF, PF, FL, and GB contributed to data acquisition. AZ contributed to data analysis. CO, GF, IC, AMO, EP, MCF, PF, FL, and GB contributed to drafting the manuscript. All authors reviewed and approved the final manuscript.
Ethics approvalThe study was conducted in accordance with the Declaration of Helsinki and was approved by the institutional review board of Fondazione IRCCS San Gerardo dei Tintori on May 23, 2024 (approval No. 546).
Declaration of generative AI and AI-assisted technologies in the writing processArtificial intelligence was not used in the conduct or writing of this study.
FundingNone declared.
Conflicts of interestDr Chukwuma Okoye reports consulting fees from Eli Lilly. Prof Fabrizio Luppi reports consulting fees from Boehringer Ingelheim. The other authors declare no conflicts of interest.
The authors thank Dr Julia Miksza, Dr Miriam Sermisoni, Dr Tommaso Finco, Dr Laura Galbusera, Dr Annalisa Sironi, Dr Flavia Sandi, Dr Francesca Pisani, and Dr Greta Tavecchi for their support in the organization and conduct of the study.
The following are the supplementary data to this article:


articles







Archivos de Bronconeumología follows the Recommendations for the Conduct, Reporting, Editing and Publication of Scholarly Work in Medical Journals
